 Eduardo Roxius

Ebenbuild develops patient-specific lung simulations: digital twins that help clinicians, nurses, and researchers understand how air, pressure, and oxygen behave inside the lungs.
The platform focuses on acute respiratory distress syndrome (ARDS), a life-threatening condition where fluid-filled lungs struggle to get enough oxygen into the bloodstream. During COVID-19, ARDS became a daily reality in intensive care units, making ventilation decisions both critical and risky.
As a UX Designer at Daylight Design, I worked on Ebenbuild with a strong focus on prototyping complex workflows. Alongside this, I supported research, concept development, and close collaboration with clinicians and scientists.
Radically new technology such as ours is toothless if no one wants to use it and very few can already imagine its possibilities. Daylight has made these possibilities remarkably tangible and has already sparked people’s imagination.
Dr. Kei W. Müller, Co-Founder and CEO, Ebenbuild
The challenge
Designing a digital twin of the lung comes with very real consequences.
If oxygen levels are set too low, the body doesn’t get enough oxygen.
If they’re set too high, the lungs can be damaged by oxygen toxicity.
Too much pressure can overstretch fragile lung tissue and cause lasting injury.
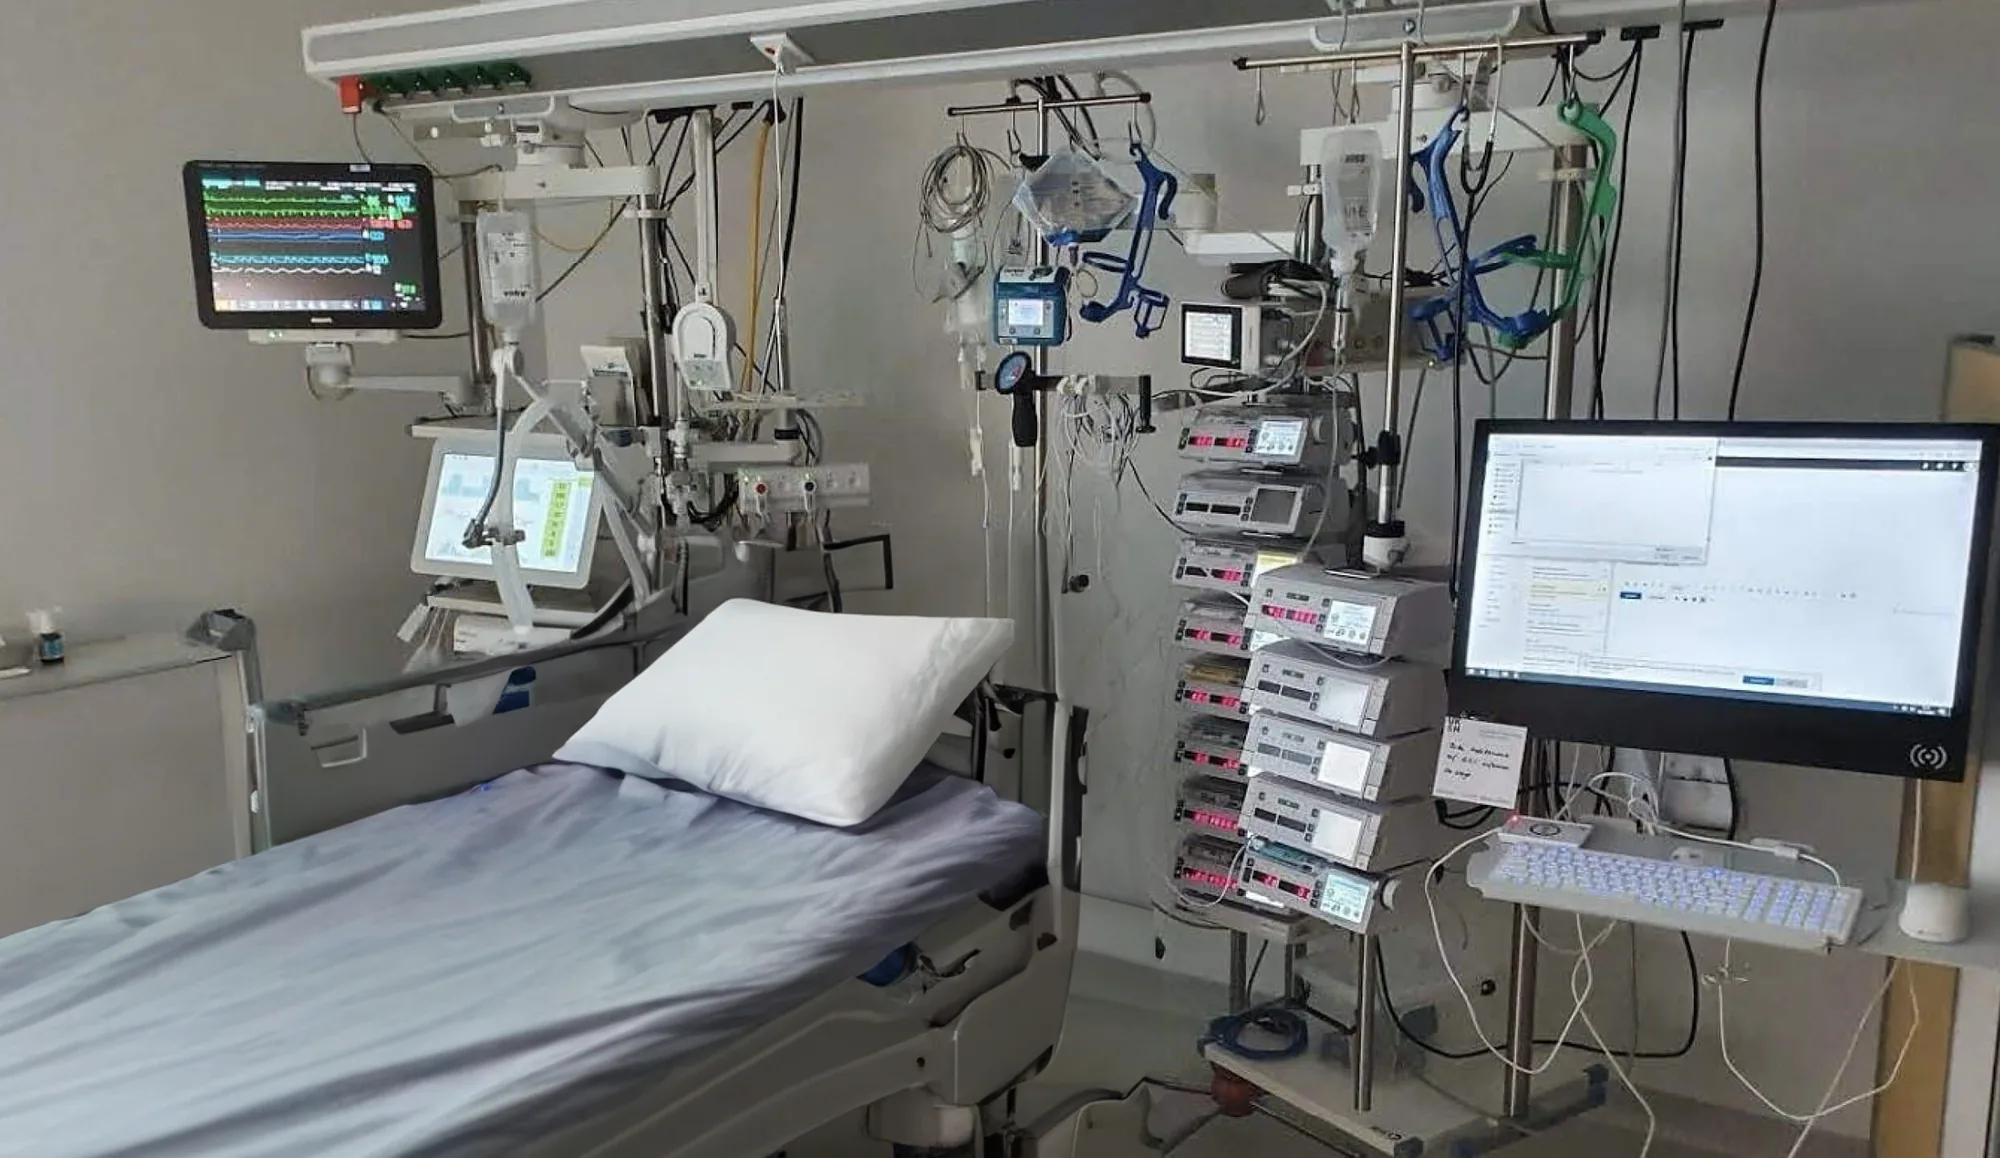
These risks are well understood in intensive care, but translating them into software is hard.
- High-risk settingsThe same controls that help save lives can also cause harm if misunderstood.
- Delayed effectsDamage may only appear hours, days, or weeks later.
- No room for confusionEven expert users need to clearly understand what a setting does before trusting the outcome.
The approach
- Prototyping to reveal risk
Prototypes were used to explore how users interpret ventilation settings and to surface misunderstandings early.
- Making cause and effect clearer
The interface focused on helping users understand what would likely happen to the lungs when a value changes, not just showing numbers.
- Supporting safe exploration
Clear structure, sensible defaults, and contextual cues were designed to prevent accidental misuse without restricting expert freedom.
- Close clinical collaboration
Continuous feedback from clinicians kept the design close to real ICU thinking and decision-making.
What the work enabled
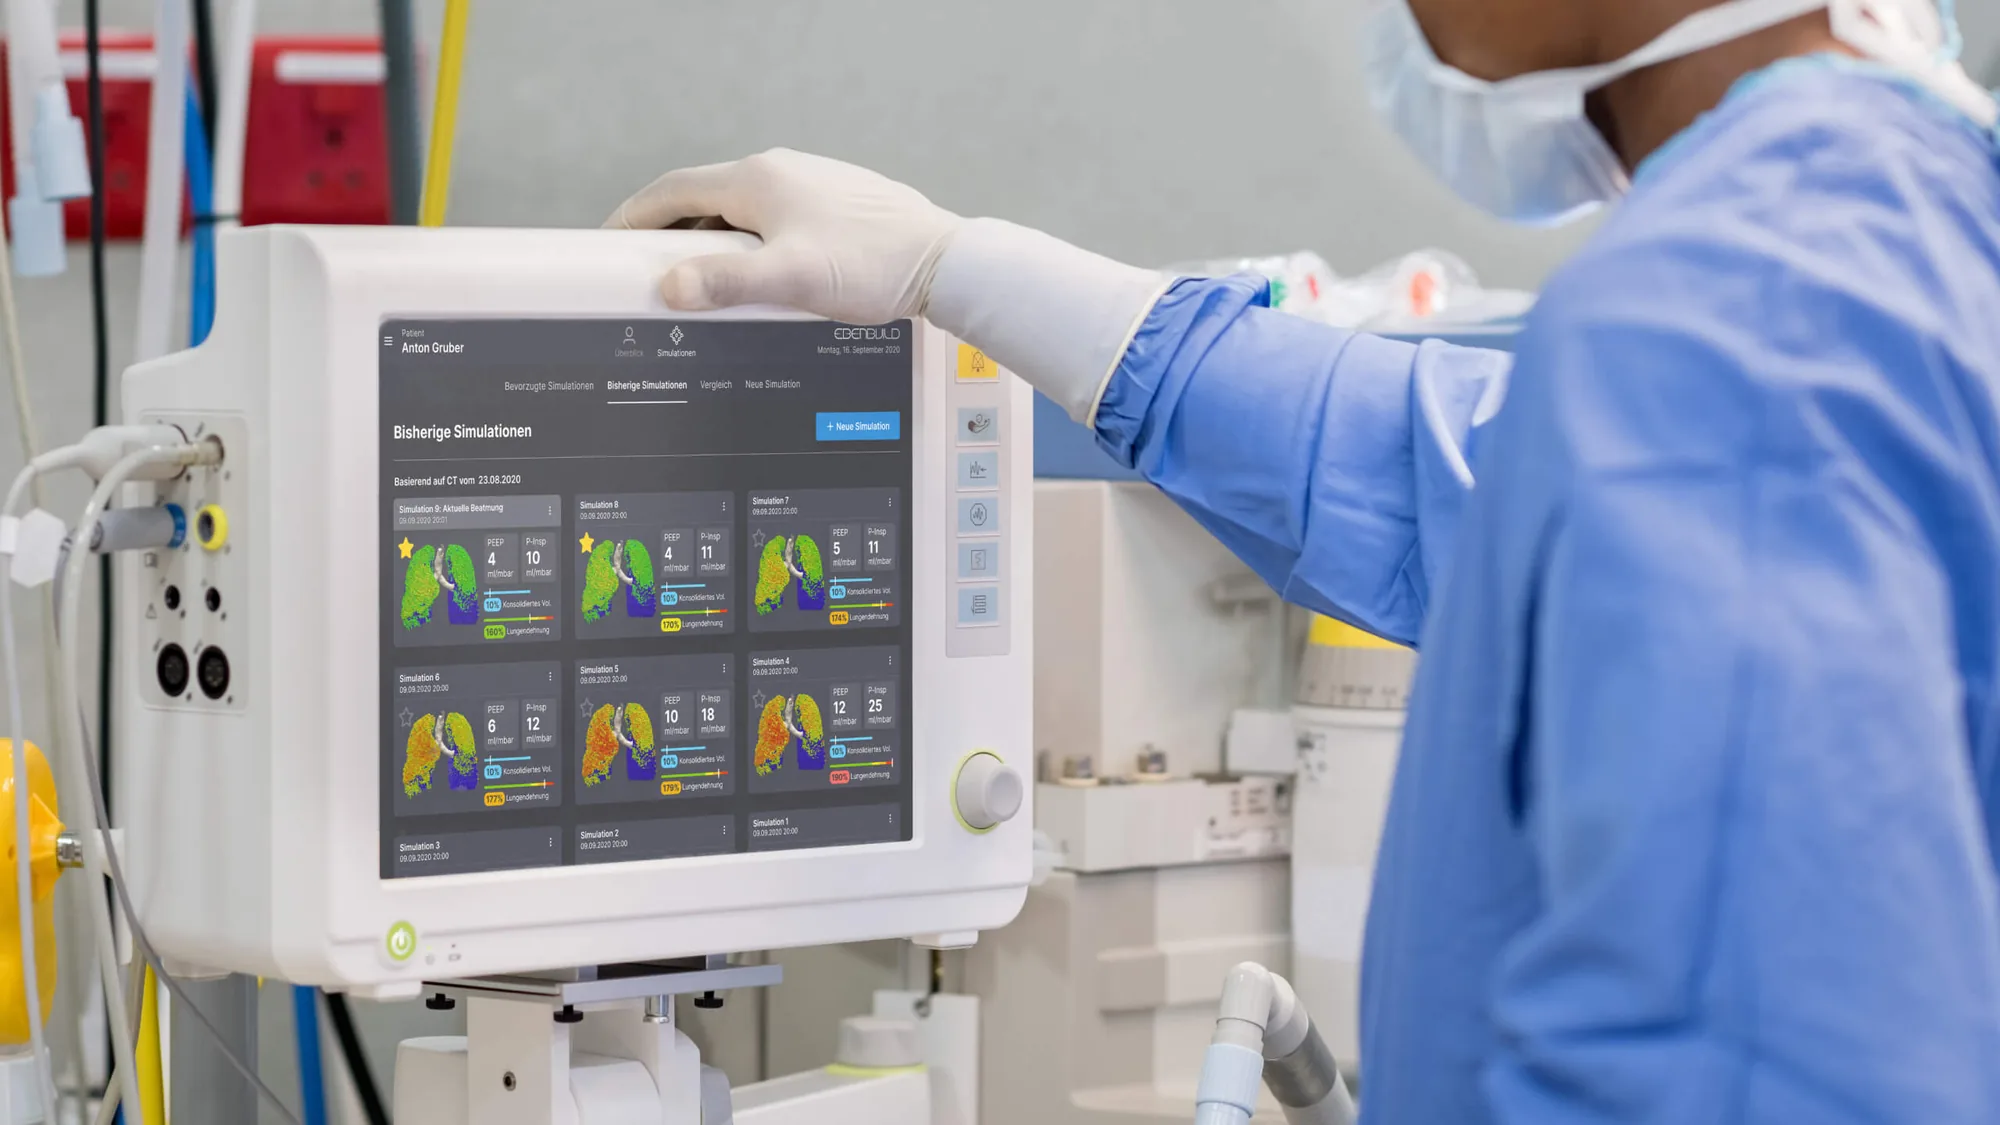
I prototyped the workflows for setting up a simulation for one patient, reviewing earlier simulations, and comparing two of them side by side. The prototypes gave clinicians and scientists a concrete interface to react to. They also gave Ebenbuild a way to show what its technology could do before most people could picture it.
Reflection
- What I learned
In medical software, UX decisions directly affect safety and trust. Clear language and structure are part of patient protection.
- What I’d do differently
I would explore more ways to show long-term impact earlier, helping users better understand how small decisions can affect lung health over time.